

What Happens to Your Body During Stem Cell Therapy? Picture yourself sitting in an infusion chair, watching a clear bag of solution slowly empty through a line into your arm. The room is quiet. The nurses are calm. And you’re left wondering what is actually happening inside your body right now. It’s a completely reasonable question, and most patients don’t get a satisfying answer before their treatment day arrives.
Stem cell therapy is not a single event. It is a biological sequence that your body actively participates in from the first minute the cells enter your bloodstream. Your immune system responds, tissues signal each other, and repair begins at the cellular level. Understanding that sequence changes the experience entirely, from something abstract and anxiety-inducing to something you can track and follow.
This article walks through that sequence step by step, covering two main approaches: hematopoietic stem cell transplants (bone marrow transplants), which are used primarily for blood cancers and disorders, and mesenchymal stem cell (MSC) infusions, which target degenerative, inflammatory, neurological, and autoimmune conditions. Clinics like STEMLIFE CLINIC in Guadalajara, Mexico, use the MSC approach with cells derived from umbilical cord tissue, structured across clearly defined phases from your very first evaluation call through post-treatment follow-up. While both pathways share some common trafficking and immune-interaction processes, they operate through fundamentally different principal mechanisms, a distinction that matters when you’re trying to understand what your body is doing at each stage.
In a bone marrow transplant, the preparation phase is significant and physically demanding. Patients go through a conditioning regimen, typically high-dose chemotherapy, sometimes combined with total body irradiation. This is not optional, and it is not incidental. Conditioning destroys marrow hematopoietic cells and suppresses immunity, producing profound cytopenias and increased infection and organ toxicity risk. The result is a body that is highly vulnerable during this window, which is exactly why this phase carries real clinical weight.
Mesenchymal stem cell therapy requires no such conditioning. The pre-treatment phase is far less intense: a clinical evaluation that typically includes detailed blood work, a full medical history review, and in some cases relevant imaging. This evaluation is not a formality. It directly determines your treatment protocol, including the number of cells administered, the delivery method, and the session frequency. Cell dosage is not applied uniformly across all patients; it is calibrated to your condition, your inflammatory markers, and your overall health profile. The evaluation also screens for exclusion criteria that protect patient safety, which is why a thorough intake process is a sign of quality, not bureaucracy.
The infusion process for MSC therapy is quiet by most accounts. Cells are suspended in a preservation solution and administered intravenously through a peripheral line or central catheter, typically over 30 minutes to a few hours, depending on the volume and protocol. Most patients report feeling little beyond a mild coolness at the infusion site. Some patients who receive cryopreserved cells report a faint, transient odor from the preservation solution, a sensory detail documented in clinical infusion reports, though reactions vary and most patients notice nothing unusual.
The physical experience is far more subdued than most patients expect. There is no dramatic sensation when the cells enter circulation. Patients typically do not feel the cells entering the bloodstream, though the biological fate of those cells is more complex than a standard IV solution: rather than being absorbed passively, they circulate actively, engage vessel walls, and begin navigating toward areas of tissue damage through a guided biological process described in the next section.
Throughout the infusion, the clinical team monitors vital signs continuously, blood pressure, pulse, oxygenation levels, and your overall presentation. They are watching for immediate reactions including fever, chills, nausea, or any sign of a mild allergic response. If any early signal appears, trained staff can slow the infusion rate or pause it entirely while the situation is assessed. This is exactly why the clinical infrastructure of the facility matters as much as the quality of the cells. Proper monitoring is not a luxury; it is what allows early detection to stay early.
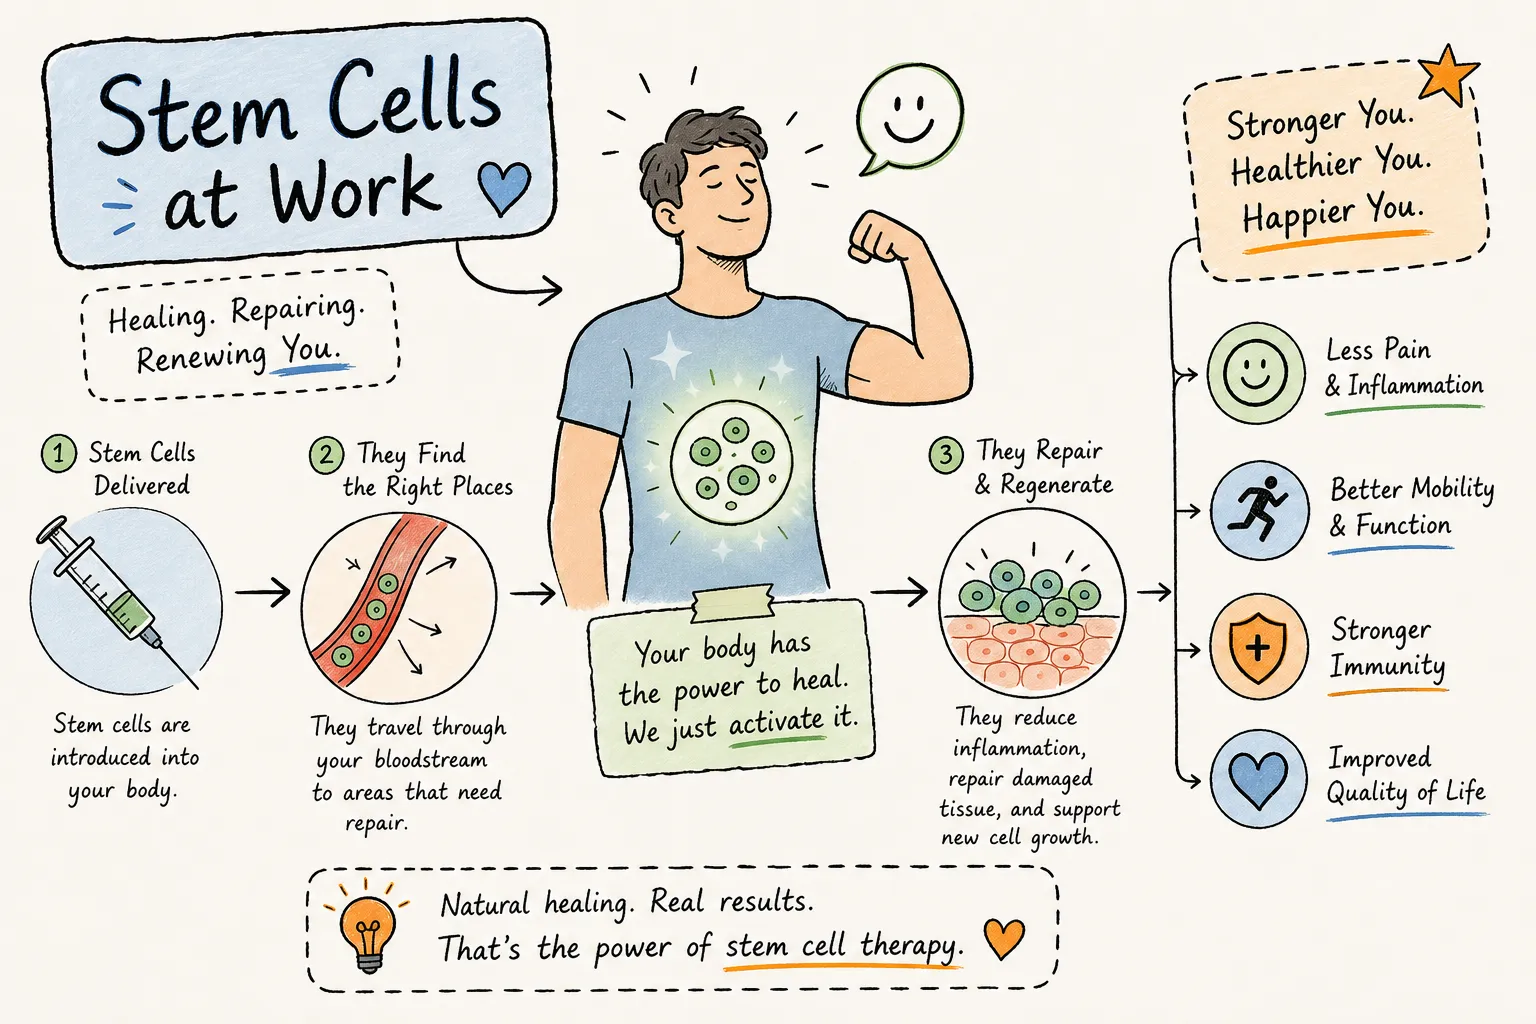
Once MSCs enter the bloodstream, they do not simply drift randomly through the body. They follow a biochemically guided process called homing, a multistep sequence that mirrors how immune cells navigate to sites of injury. Damaged or inflamed tissue releases chemical signals including SDF-1/CXCL12, PDGF-AB, and other chemokines. These signals activate adhesion molecules on the inner walls of blood vessels near the injury site, which allows the circulating stem cells to tether, slow, adhere firmly, and then migrate through the vessel wall into the surrounding tissue.
In preclinical models, the degree of inflammation at the target tissue appears to influence how many cells arrive there. More active injury produces stronger chemical gradients, which attract more cells. This is one reason why MSC therapy tends to be most measurable in patients with documented inflammation or tissue damage rather than as a purely preventive measure in healthy individuals.
During this window, cells are circulating, beginning to adhere to vessel walls near areas of damage, and releasing signaling molecules even before any formal tissue integration occurs. Anti-inflammatory effects can begin showing up in inflammatory markers within the first 24 to 48 hours, though patients rarely notice functional changes this early. What you may feel during this period is mild fatigue, a low-grade fever, or flu-like symptoms including headache or chills. These are not signs that something has gone wrong. They reflect your body’s recognition that new biological material is interacting with tissue, and the immune system is paying attention.
The repair process after MSC therapy runs through two dominant mechanisms and one smaller contributor. Paracrine signaling is the most significant: infused cells secrete growth factors including VEGF, HGF, and FGF-2 that instruct surrounding cells to regenerate, promote new blood vessel formation, and reduce programmed cell death in damaged tissue. Immune modulation works alongside it, MSCs shift the local immune environment away from chronic inflammation, which is what blocks natural repair in conditions like rheumatoid arthritis, lupus, and COPD. Beyond these two, direct differentiation, where cells convert into the tissue type they are repairing, plays a smaller but real role in MSC therapy compared to the paracrine and modulatory effects.
For hematopoietic stem cell transplants, the dominant mechanism is fundamentally different: direct engraftment and differentiation into blood and immune cell lineages. The goal is to rebuild the hematopoietic system from scratch. MSCs and HSCs work through distinct biological pathways, even though both fall under the broad label of stem cell therapy.
In a hematopoietic transplant, engraftment is the critical milestone. It is defined as the point at which donor cells have established themselves in the marrow and blood counts begin rising. The standard clinical marker many transplant centers use is an absolute neutrophil count (ANC) reaching 500 for three consecutive days. Neutrophil engraftment typically occurs between day 10 and day 21 after infusion, with platelet recovery following several days to weeks later.
For MSC therapy, the improvement timeline looks completely different. There are no blood count markers to track in the same way. Progress is measured through symptom reduction, mobility changes, pain levels, and inflammatory marker panels over weeks to months. Early biological effects may appear within days, but functional improvements, better joint mobility, reduced pain, improved energy, generally become apparent over a window of four to twelve weeks and continue developing beyond that, with timing varying by condition and individual response.
The most commonly reported side effects in the first 72 hours after MSC therapy are transient fever, fatigue, headache, and mild chills. These are the body’s inflammatory response to new cells interacting with tissue. They are expected, manageable, and temporary. For most patients, they resolve within one to three days without any intervention beyond rest and hydration.
For hematopoietic transplants, the risk window is more serious. During the period of very low blood counts following conditioning, neutrophil levels drop to near zero, which means the immune system cannot mount a defense against infection. Any fever during this period requires immediate contact with the care team. This is not a situation where you wait to see if symptoms resolve on their own. Fever during the neutropenic window is treated as urgent until proven otherwise.
Graft-versus-host disease (GVHD) is a complication exclusive to allogeneic transplants, those that use donor cells. In this scenario, donor immune cells enter the recipient’s body and recognize host tissues as foreign, then begin attacking them. The skin, liver, and gastrointestinal tract are the most commonly affected. Acute GVHD can develop within the first 100 days after transplant; chronic GVHD can persist for months or years and requires ongoing management.
Autologous therapy carries no GVHD risk because the immune system does not target its own cells. Cord tissue-derived MSCs, the type used at STEMLIFE CLINIC, are considered low-immunogenicity because they express fewer of the surface markers that trigger aggressive immune recognition. This does not mean the immune response is zero, but the immune reaction they trigger is substantially less intense than with many other allogeneic sources, which is one reason this cell type is well-suited for international patients managing complex chronic conditions.
After the infusion ends, responsible clinics do not immediately discharge you. A post-infusion observation period gives the clinical team time to track any delayed reactions that develop over hours rather than minutes. Vital signs continue to be monitored, and any response that emerges during this window is managed before you leave the facility. The immune system’s reaction to new cells has a timeline of its own, and early detection during this period allows for fast, effective management when it is needed.
Post-treatment follow-up is where the ongoing story of your recovery gets tracked. Scheduled appointments, laboratory work to monitor inflammatory markers and immune response, and direct access to the clinical team between visits are all part of responsible regenerative care. At STEMLIFE CLINIC, the post-treatment protocol is structured specifically to catch delayed responses, track functional improvement over time, and adjust care recommendations based on how each individual patient’s body responds. That last part matters: a standard checklist is not a protocol. A protocol adapts to you.
From preparation through infusion, homing, the healing response, and recovery, your body is an active participant in stem cell therapy. It is not a passive recipient of a treatment done to it. Every phase involves your tissues, your immune system, and your biology working in response to the cells that have been introduced. Understanding what exactly happens to your body during stem cell therapy gives you a clearer picture of what to watch for, what is expected, and when something genuinely needs attention from your care team.
Most patients report that the experience was less overwhelming than they expected, not because the biology is simple, but because understanding it in advance makes it trackable. The clinical evidence in regenerative medicine continues to grow, and the experience is far more manageable than most people imagine before their first conversation with a specialist. If you are living with a chronic, degenerative, or autoimmune condition and want to understand whether your situation makes you a candidate for this kind of treatment, an initial evaluation with a specialist at STEMLIFE CLINIC costs nothing and gives you clinical information specific to your case, which is a more useful starting point than generalized research.