

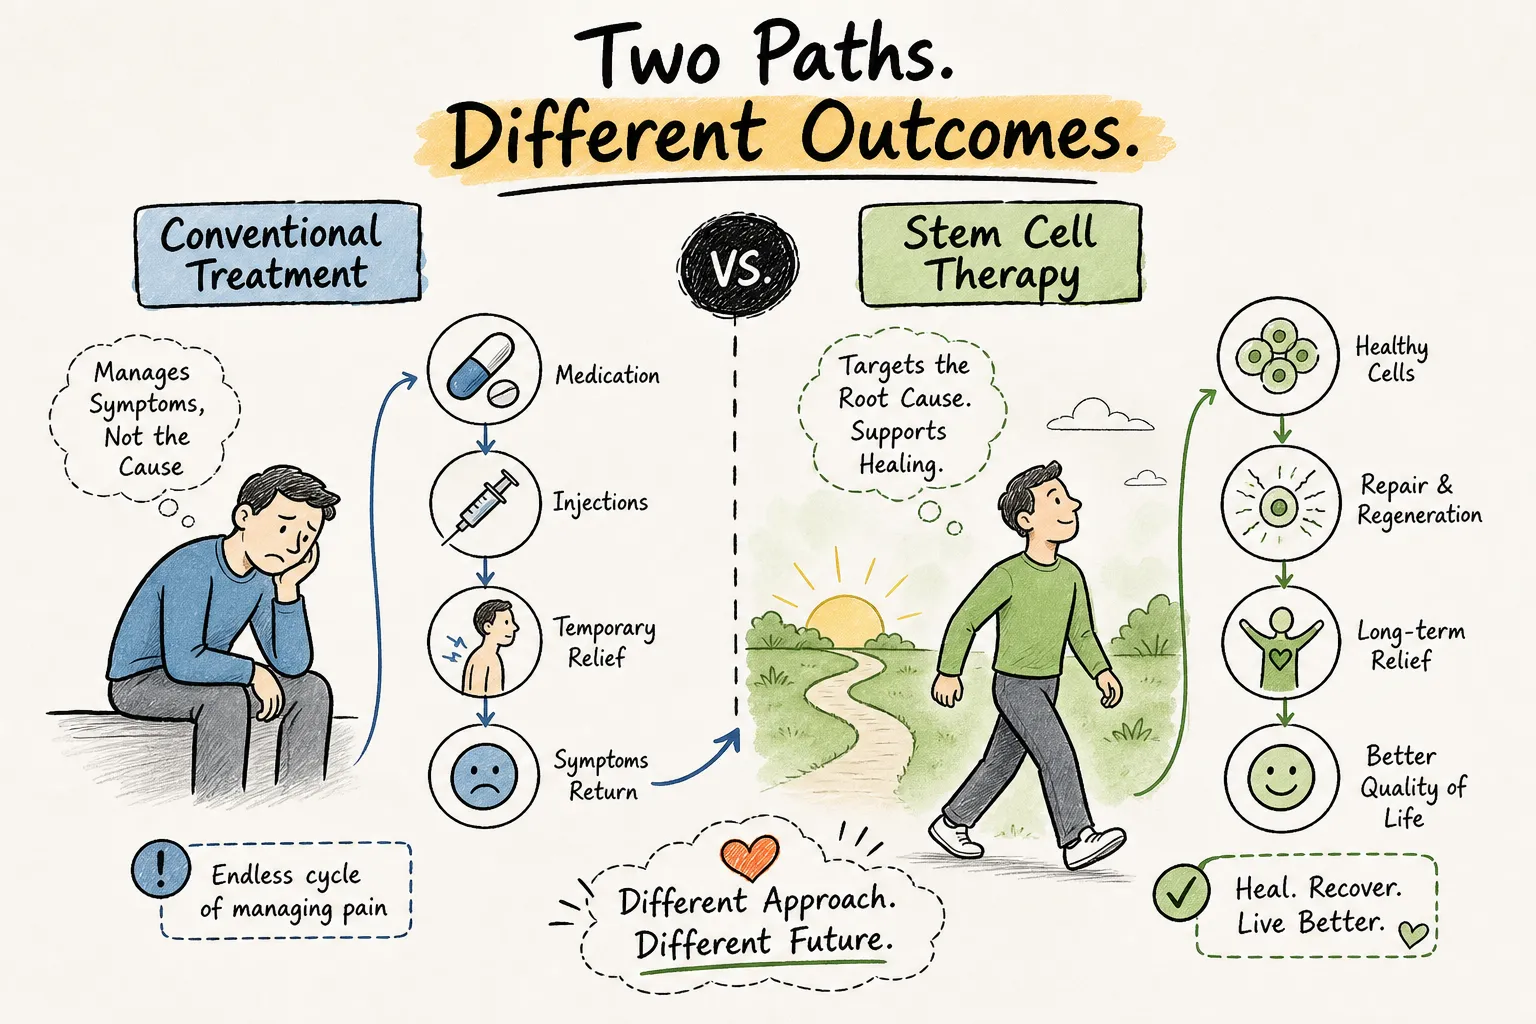
After years of managing a chronic condition, many patients arrive at a quiet frustration: the medications are working, technically, but the pain comes back when a dose is missed, mobility stays limited, and the underlying tissue keeps deteriorating. Surgery may have fixed a structural problem but didn’t restore what was lost. This gap between symptom control and actual biological recovery is exactly what drives people to research regenerative medicine, and to ask a question that deserves a serious answer: how is stem cell therapy different from conventional medical treatments, and does that difference actually matter for someone in their situation?
The short answer is mechanism. Conventional treatments block, suppress, or reconstruct. Stem cell therapy communicates: it introduces living material that reads the tissue environment and releases signals that shift the body toward repair. That distinction shapes how procedures are performed, how recovery unfolds, and what long-term outcomes look like, in measurable ways that go well beyond marketing language. STEMLIFE CLINIC, a regenerative medicine clinic in Guadalajara, Mexico, works with patients navigating exactly this question, connecting the science to practical, personalized clinical decisions.
This article walks through the core mechanistic difference, what recovery actually looks like, where the clinical evidence is strongest, how long benefits tend to last, and what you need to ask before walking through any clinic’s door.
Pharmacologic treatments work by binding a molecular target. NSAIDs inhibit the COX enzymes that produce prostaglandins. Corticosteroids bind glucocorticoid receptors and suppress transcription of inflammatory genes. Biologic DMARDs are engineered proteins that neutralize specific cytokines like TNF or IL-6. Each of these approaches is precise and, for many patients, genuinely effective. Every one of them works through a fixed biochemical target, and none introduces living material that can respond to the tissue around it.
Surgery takes a different approach entirely: it acts mechanically, removing damaged tissue, repairing structural defects, or replacing worn-out joints with prosthetics. When a surgeon performs a total knee replacement, the structural problem is addressed directly. What surgery cannot do is trigger the cellular signaling cascades that lead to genuine tissue regeneration, and that gap is precisely where regenerative approaches enter the conversation.
Mesenchymal stem cells (MSCs) work primarily through what researchers call paracrine signaling. Rather than becoming replacement tissue themselves in most applications, they secrete a broad mix of growth factors, cytokines, and extracellular vesicles that change the local environment. This secretome can reduce pro-inflammatory mediators, shift macrophages from a destructive inflammatory state toward a repair-oriented one, promote new blood vessel growth, and protect surviving cells from further damage.
The adaptive nature of this process is what makes it mechanistically distinct from conventional pharmacologic or surgical care. MSCs sense the inflammatory cues around them and adjust what they release in response. A single cell product can simultaneously influence immune activity, inflammation, and tissue repair, acting as a biological coordinator across multiple repair pathways rather than locking onto a single receptor. That’s a fundamentally different treatment model, and it’s the core of what makes stem cell vs conventional treatment comparisons worth taking seriously.
A total knee replacement involves general or regional anesthesia, a surgical incision, a hospital stay, and a structured rehabilitation program that begins almost immediately and continues for months. A mesenchymal stem cell procedure is typically an intravenous infusion or a targeted intra-articular injection, performed as an outpatient in a single session or short series of sessions. Patients walk out the same day in most cases.
Procedure-related discomfort after an MSC injection is usually mild: some soreness at the injection site, possible fatigue for a few days. Meaningful changes in pain and mobility typically begin to emerge over two to twelve weeks, with larger gains appearing by three to six months as the biological process unfolds, a timeline that varies by condition, cell product, and delivery route. This looks and feels very different from the immediate structural correction that surgery provides, but it’s also measured against a very different recovery burden.
When a patient undergoes surgery, the body is simultaneously managing recovery from the procedure itself and the underlying condition. For older patients or those with comorbidities like diabetes or cardiovascular disease, that double burden carries real surgical risk. Because a stem cell procedure doesn’t mechanically disrupt tissue, the body isn’t recovering from a procedural injury on top of everything else. That makes the regenerative path particularly relevant for patients who are not ideal surgical candidates but still need an active intervention beyond medication management.
Knee osteoarthritis is the best-supported indication in the current randomized controlled trial literature. Multiple meta-analyses report statistically significant reductions in pain scores (including WOMAC and VAS) and improvements in physical function, with some evidence of cartilage-volume benefit at twelve months in specific imaging studies. A 2024 systematic review found that 73% of clinical outcome measures improved with MSC therapy versus control in autologous studies at one year.
Study heterogeneity is real: trials differ in cell source, dose, delivery method, and comparator, which limits certainty. One notable counterpoint analysis (Pas et al., 2017, British Journal of Sports Medicine) concluded MSC injection provides little to no improvement in pain at three to six months. The honest picture is a consistent signal of benefit with moderate-quality evidence, enough to inform a clinical conversation, but not to guarantee outcomes for any individual patient.
For ischemic stroke, some meta-analyses find improved functional outcomes at 90 days and one year, with more patients reaching favorable neurological status scores. In ischemic heart disease, randomized trial data show modest improvements in left ventricular function beyond standard medical therapy. These are promising signals, not established standards of care, and the evidence quality in these areas is generally low to moderate.
Autoimmune conditions, metabolic disease, and frailty represent active research areas. A phase II randomized double-blind trial (Tompkins et al., 2019, published in The Journals of Gerontology) for aging-related frailty reported improvements in physical performance and inflammatory biomarkers. Patients considering stem cell therapy for these conditions should understand they are in investigational territory, and any credible clinic should say so directly, including how they track outcomes after treatment.
Most chronic disease patients on pharmacologic treatment manage symptoms indefinitely. NSAIDs, DMARDs, and immunosuppressants require ongoing use, dose adjustments over time, and monitoring for systemic side effects. The underlying condition often continues to progress despite medication, which is why many patients feel like they’re on a treadmill, controlling today’s symptoms while tomorrow’s deterioration keeps advancing. That lived experience is what makes a therapy with a different durability profile worth evaluating carefully.
In knee osteoarthritis and ischemic stroke, some studies report benefit extending to one year and beyond. The biological rationale holds up: if paracrine signaling successfully modulates an ongoing inflammatory cycle or promotes genuine tissue repair, the benefit may outlast the presence of the cells themselves. This is not a guarantee of permanent effect, but it represents a qualitatively different durability profile than a drug that stops working when you stop taking it.
Not every patient responds the same way, and that’s not a caveat to brush past. Disease stage, cell source (autologous versus allogeneic), delivery route, and baseline inflammatory burden all influence how long and how deeply benefit lasts. Personalized treatment protocols that account for the full clinical picture, not a one-size-fits-all cell dose, are what separate durable outcomes from short-term effects. Durable outcomes depend on matching the protocol to the patient’s specific biology, which is why thorough candidacy evaluation before any treatment plan is proposed is a defining feature of responsible regenerative care.
For allogeneic MSC therapy in clinical settings, the realistic risk profile includes local pain and swelling at the injection site, mild fatigue, and transient fever, all generally short-lived. Serious adverse events reported in peer-reviewed trials include:
Large meta-analyses of MSC trials have not found a consistent increase in treatment-related serious toxicity versus controls, but the risks are real and should be discussed explicitly with any provider. The most serious adverse events in the published literature, including blindness, paraplegia, tumor formation, and death, have been reported primarily in the context of unapproved or heavily manipulated interventions outside clinical protocols. That distinction is critical when choosing a provider.
In the United States, approved stem cell-based therapies are concentrated in hematologic diseases: hematopoietic stem cell transplantation for blood cancers, approved cord blood products, and a small set of engineered cell/gene therapies for conditions like sickle cell disease and steroid-refractory graft-versus-host disease. Orthopedic, neurological, and autoimmune applications remain investigational in the United States as of 2026. The FDA has not approved stem cell products for osteoarthritis, tendon injuries, or general regenerative uses, and explicitly advises caution toward clinics claiming otherwise.
Before committing to any regenerative medicine provider, ask these directly:
Clinics that operate within defined clinical protocols, obtain formal informed consent, and document follow-up systematically are operating in a fundamentally different category from unregulated operators. When evaluating any clinic, including STEMLIFE CLINIC, these are the markers that matter: candidacy evaluation before any treatment is proposed, structured protocols for each condition, and follow-up that extends well beyond the procedure itself.
The strongest candidates for regenerative medicine are people with degenerative, inflammatory, or autoimmune conditions where conventional treatment has reached a ceiling, who are not in an acute surgical emergency, and who are prepared to engage with a structured multi-step protocol. Disease stage matters significantly: earlier intervention in a degenerative condition generally produces better regenerative outcomes than treating tissue that has reached end-stage damage. If you have knee osteoarthritis and are still a candidate for conservative management, regenerative therapy may be more effective now than after a decade of further degeneration.
A credible starting point is a clinical review that takes your full history seriously: current diagnosis, imaging results, lab work, medications, and everything you’ve already tried. STEMLIFE CLINIC offers an initial online evaluation for international patients, structured as a genuine candidacy assessment to determine whether your specific condition and health profile align with what regenerative medicine can currently offer, before any travel or treatment commitment is made. For patients based in Spain or other parts of Europe, that preliminary step clarifies whether pursuing treatment in Mexico makes clinical sense for their situation.
Conventional medicine excels at what it was designed to do: target specific inflammatory pathways, address structural damage directly, and manage symptoms with reliable pharmacologic precision. What it rarely does is activate the biological repair process itself. Stem cell therapy, specifically MSC-based therapy working through paracrine signaling, operates on a different logic: it introduces living material that reads the tissue environment and shifts it toward healing, rather than blocking a pathway or reconstructing anatomy.
The differences in mechanism, recovery experience, and long-term durability are real, and so are the current limitations. When asking how stem cell therapy differs from conventional medical treatments, the honest answer is that the evidence is strongest for knee osteoarthritis (where multiple meta-analyses show consistent benefit with moderate-quality evidence), promising but not yet definitive for stroke and cardiac disease, and investigational in many other conditions. That spectrum means choosing the right clinic and undergoing a genuine candidacy evaluation are not optional steps; they are the entire foundation of a responsible decision.
For patients who have reached the ceiling of standard options, stem cell therapy represents a different philosophy of care, one centered on restoring function rather than managing decline. Understanding how is stem cell therapy different from conventional medical treatments, and then evaluating your own situation against the best available evidence, is what makes the next step worth taking.